Why opioids are hard to quit
Your body makes its own opioids. Endorphins and related molecules dull pain, settle stress and give the quiet sense that things are all right. They act on opioid receptors, above all the mu-opioid receptor. Oxycodone, hydrocodone, morphine, heroin and fentanyl act on the same receptor, only far more strongly. Pain fades, worry goes soft, and for a while nothing is urgent.
Taken every day, opioids teach the nervous system to push back. Receptors become less responsive and some are pulled from the cell surface. Other systems speed up to compensate. This is tolerance: the same dose does less, so the dose goes up. It is also dependence: take the drug away and the compensation is left running with nothing to balance it. That is withdrawal, and avoiding it soon becomes a reason to keep using in itself.
The supply has changed the stakes. Most of the street opioid supply in the United States now contains fentanyl, often in pills pressed to look like oxycodone. The dose in any pill or bag is unknowable. That is why overdose deaths stayed so high even as prescriptions fell, and why every plan to quit has to include a plan to stay alive.
Withdrawal, day by day
Opioid withdrawal is rarely dangerous in a healthy adult, but it is miserable, and the misery is what pulls people back. Expect aches deep in the muscles and bones, sweats and chills, gooseflesh, yawning, a running nose and eyes, stomach cramps, diarrhea, vomiting, restless legs, anxiety and almost no sleep. Vomiting and diarrhea can dehydrate you, which is the real medical risk.
| When | What most people feel |
|---|---|
| 8 to 24 hours | With short-acting opioids such as heroin, oxycodone or fentanyl: anxiety, yawning, sweating, running nose, the first craving. |
| Day 1 to 3 | The peak. Aches, chills, cramps, diarrhea, vomiting, restless legs, no sleep. |
| Day 4 to 7 | The acute phase eases for most people. Exhaustion, poor appetite and broken sleep remain. |
| Methadone and buprenorphine | Withdrawal starts later and lasts longer, often well past the first week. |
| Weeks to months | Post-acute symptoms: low mood, anxiety, poor sleep, low energy, cravings under stress. This is the stretch where most relapses happen, and where lost tolerance makes them most dangerous. |
If you feel hopeless or think about ending your life, call or text 988 in the United States. That feeling is common in withdrawal, and it passes.
What works without iboga
Opioid use disorder has the best-studied treatments in addiction medicine, and they save lives. Buprenorphine and methadone, taken long term, cut the risk of overdose death sharply and help people rebuild stable lives. Extended-release naltrexone, a monthly injection that blocks opioid receptors, is a third option for people who have already stopped. These medications are the evidence-based standard. If one of them is working for you, that is a success, not a stepping stone.
Iboga is for a different person: someone who wants to stop opioids altogether, including maintenance medication, and has weighed that choice with their own doctor. Whichever path you choose, these steps help:
- Carry naloxone. Naloxone (Narcan) reverses an opioid overdose and is sold over the counter. Keep it with you and show the people around you where it is.
- Never use alone. If you are still using, have someone present who can call for help.
- Get a doctor involved in the stop. Withdrawal can be eased with medications such as lofexidine or clonidine, and a doctor can start buprenorphine if you decide to.
- Tell someone. Shame keeps opioid use hidden. One person who knows changes the odds.
The free SAMHSA National Helpline (1-800-662-4357) can point to local treatment, including buprenorphine and methadone providers.
How it works, in motion
Four stages, one meter of how good everyday life feels: the rush of a dose, the flatline that follows, the reset the iboga night may open, and what matters after. Press play, or tap a stage.
How it works
From the warm blanket to the root of the pain
One dose makes everything stop hurting, like nothing else can.
Fentanyl is so strong that a tiny amount can stop your breathing.
The same dose does less, and without it your whole body hurts.
Within a day come sweats, aches, cramps and sleepless nights.
After the iboga night, withdrawal is much lighter and life can feel good again.
An opening, not a cure. Your tolerance drops too, so an old dose can now kill.
Then you face what the drug was covering.
Often an injury, grief or loneliness. Around the fire, you find what you need instead.
What iboga does for the body
Opioid withdrawal is where iboga has the most evidence in people. That evidence is real, but it comes from observational studies and case series, not randomized trials. There has been no randomized controlled trial of ibogaine itself.
- Withdrawal reduced. In an observational study of 30 people treated with ibogaine in Mexico, scores on a standard opioid withdrawal scale fell from an average of 31 to 14, and half reported no opioid use at one month; at three months it was a third. A study of 14 people in New Zealand, followed for up to twelve months, found withdrawal scores lower within a day, and drug-use and depression scores lower a year later, though close to half still reported some opioid use in the past month at each follow-up.
- Craving reduced. A case series from St Kitts covering 191 people treated for opioid or cocaine dependence under medical monitoring reported reduced craving and withdrawal after a single treatment.
- In animals. Ibogaine reduced morphine self-administration in rats as early as 1991, and a 2016 systematic review of animal studies found reduced self-administration of opioids, cocaine and alcohol.
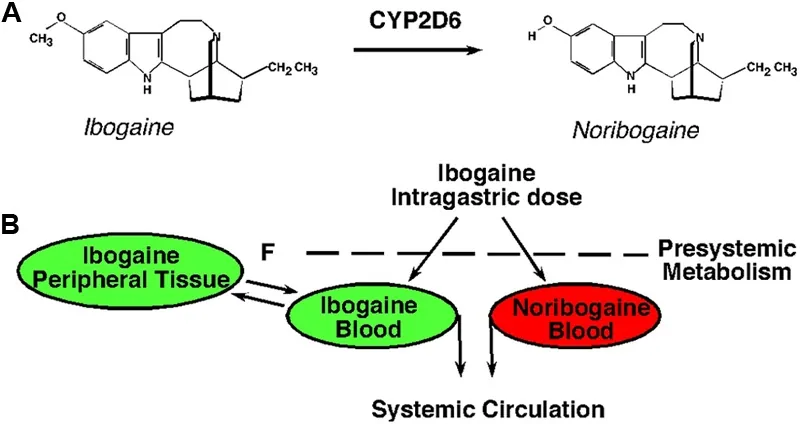
- The mechanism. Ibogaine and its long-lived metabolite noribogaine act on mu and kappa opioid receptors, NMDA receptors and the serotonin transporter, and in animal research increase GDNF, a growth factor that supports the reward system. Read How iboga works.
Two honest limits. First, noribogaine given alone in a small randomized safety trial did not significantly reduce withdrawal, though the trial was not built to test that. Second, there are no studies specific to fentanyl. The numbers, study by study, are in the research section below. What guests describe is going through the ceremony with withdrawal strongly reduced, and waking to a quiet where the craving used to be. We call that a strong opening, not a cure. The weeks after still matter.
What the ritual does for the soul
The Bwiti tradition of Gabon does not begin with the drug. It begins with the person. A dependence, in its reading, shows that some part of the self has gone untended for a long time, and the substance has settled into the place that part should hold. Taking away the substance without returning to that place leaves a vacancy, and vacancies get filled.
Opioids have a particular voice. They do not make you more; they make it stop hurting. That is why so many stories start with real pain, a body that was injured, and why so many continue because of another kind of pain: grief, trauma, loneliness, a numbness that felt safer than feeling. People speak of opioids as a warm blanket, and later as a wall between them and everyone they love. In the night, guests describe meeting what the blanket was covering, often gently, sometimes with the people they lost, and understanding why they needed it. Understanding is not the end of the work, but it changes the question from how do I stop to what do I need instead.
The ritual gives that meeting a shape. The nganga, initiated in the Missoko lineage, opens the night at the fire talk, where each person speaks their intention aloud before the fire. The medicine is given in steps, and each traveler is watched throughout. The ngombi harp and the mongongo mouth bow play through the hours; the tradition says they guide the traveler and keep the path. The practitioner's clearings and protections are the tradition's way of lifting off what was never yours to carry. At dawn the nganga closes the ceremony, and in the days that follow, what was seen in the night's life review is spoken and set in its place in your life. The tradition holds that the medicine shows you what you need, not what you want. Belief is not required. Showing up honestly is enough.
Opioids and iboga: safety
This section matters more than any other on this page.
- Lost tolerance can kill. After iboga, tolerance to opioids can drop sharply. A dose you used safely before can now be fatal. If you ever use again after the retreat, it must be treated as using for the first time: far less, never alone, naloxone in reach. Before you go home, this is part of the integration talk.
- Maintenance medication is not a quick switch. Methadone and buprenorphine stay in the body for a long time and do not combine safely with iboga. They must be switched to a short-acting opioid weeks before the retreat, planned with your prescribing doctor. In the supervised Dutch study, patients were moved to morphine first. A death has been reported after iboga taken with methadone and diazepam. Addiction medicine specialists affiliated with ASAM have warned against tapering off methadone or buprenorphine in order to take ibogaine, and we take that seriously: this is only for people who have decided, with their doctor, to stop.
- The heart. Iboga affects the heart's rhythm, and so does methadone, so every guest is screened first and monitored through every ceremony: how we protect your heart.
- Fentanyl. Street fentanyl is unpredictable and can linger in the body longer than its short action suggests. The physician plans the interval before the first dose case by case.
- Other substances. Benzodiazepines and alcohol are often used alongside opioids. Their withdrawal can cause seizures, so they are tapered or stabilized medically first, and iboga is never given during benzodiazepine withdrawal. SSRIs and bupropion can raise ibogaine levels through the liver enzyme CYP2D6 and are reviewed with the physician.
Read Safety and medical protocol and Can iboga kill you?
The program, step by step
- Discovery call and screening. What you use, how much and how often, including pills, powder, maintenance medication, benzodiazepines and alcohol; ECG and full bloodwork.
- The plan before travel. For methadone or buprenorphine, a switch to a short-acting opioid weeks ahead, coordinated with your prescribing doctor. For short-acting opioids, the physician sets the plan for the last dose.
- Arrival and stabilization. Vitals, rest, food, the first fire talk without medicine. Opioid guests usually join the fourteen-day detox program, $13,000 plus medical detox days at $600 to $800 per day; the physician decides how many.
- The first ceremony. After a short interval since the last opioid dose, planned by the physician. The physician watches the heart on telemetry; the nganga paces the doses.
- Processing and integration. Talking through the night's life review, time with the psychologist, a plan for pain if pain was part of the story, and a frank talk about tolerance and naloxone.
- Three months after. Four integration calls and the medical team reachable through the post-acute weeks. Read Cost for every program option.
Who it is for
People dependent on prescription or street opioids who want to stop entirely, who have tried tapers or detox before, and who are ready to be fully honest with a physician about what they take. People on methadone or buprenorphine who have decided with their prescriber to come off and can plan the switch. It is not for anyone with a heart condition or an ECG that cannot be cleared, anyone unwilling to follow the switch and stop plan, anyone in benzodiazepine withdrawal, or anyone sent by someone else. If maintenance medication is keeping you alive and well, keep it. The discovery call is where we work out, without judgment, whether this fits.
Questions people ask
What is the timeline for opioid withdrawal?
With short-acting opioids, symptoms usually start 8 to 24 hours after the last dose, peak over days one to three, and the acute phase eases within about five to seven days. With methadone and buprenorphine, withdrawal starts later and lasts longer. Low mood, poor sleep and cravings can continue for weeks to months.
What medication is used for opioid withdrawal?
Buprenorphine and methadone treat withdrawal and are also used long term to prevent relapse and overdose. Lofexidine and clonidine ease symptoms such as sweating, anxiety and cramps without being opioids. Doctors often add medicines for nausea, diarrhea and sleep. Tell our physician about every one of them before a retreat.
How long does it take for your brain to go back to normal after opioids?
The acute withdrawal is over in about a week, but mood, sleep, energy and the ability to enjoy ordinary things usually recover over months. Many people feel clearly better within three to six months; for some, after long or heavy use, it takes longer. Sleep, exercise, food and steady support all help.
What is the 7 day rule for opioids?
It usually means one of two things. Many states limit a first opioid prescription for short-term pain to about seven days. In treatment, it often refers to the opioid-free period, commonly around seven to ten days after short-acting opioids and longer after methadone or buprenorphine, needed before starting naltrexone, which would otherwise trigger sudden withdrawal. Your doctor sets the exact interval. Iboga follows its own plan, set by our physician.
Does ibogaine stop withdrawals?
For opioids, the evidence says it strongly reduces them. In a Mexican study of 30 people, withdrawal scores fell from 31 to 14 on average, and a New Zealand study of 14 people found withdrawal scores lower within a day of treatment. Staying off opioids afterwards was harder: many people used again within months. Some symptoms can remain, and none of these studies were randomized. It requires medical screening and cardiac monitoring.
What reduces withdrawal symptoms?
Medically, buprenorphine or methadone, or lofexidine and clonidine for symptoms. At home: fluids with salts, simple food, warm baths, light stretching for restless legs, a cool dark room, and someone with you. A gradual taper with a doctor is gentler than a sudden stop.
Does caffeine help with opiate withdrawal?
Not really. A morning coffee can lift the fog a little, but caffeine tends to worsen the anxiety, sweating, stomach upset and insomnia that withdrawal already brings. Keep it small and early in the day, and drink plenty of water.
Does Benadryl help opiate withdrawal?
Some people use it for sleep and a running nose, but it can make restless legs worse, causes grogginess and confusion at higher doses, and is risky combined with other sedatives. Ask a doctor before using it, and tell our physician if you take it before a retreat, since it can interact with other medicines.
What are the hardest addictions to quit?
Opioids, nicotine, alcohol, benzodiazepines and stimulants are usually named. Opioids stand out because withdrawal is so physically intense and because relapse after a period of abstinence carries a high overdose risk. That is also why opioids have the most effective medications of any addiction.
Can I come to a retreat if I am on Suboxone or methadone?
Only if you have decided with your prescribing doctor to come off, and only after switching to a short-acting opioid weeks before travel. Never stop either medication suddenly on your own. If maintenance treatment is working for you, staying on it is a sound choice.
Keep reading
 The programAddiction and detox programMedical stabilization, Bwiti ceremonies, a physician on site, and three months of care.20 min read
 The programSafety and medical protocolThe risks, the screening, what happens around your mat, and who we decline.13 min read
 Mind and bodyCan iboga kill you?What the literature says about deaths, the five causes, and what prevents them.9 min read
 Mind and bodyIbogaine success ratesWhat the studies measured, what they found, and how to read a claim.7 min read
 SubstancesHow to quit kratom and 7-OHOpioid-type withdrawal, tapering, and the cautions to know before iboga.11 min read
Addiction guides
 The programRehab, ibogaine clinic or Bwiti Life?What each approach treats in the body, the emotions and the spirit.13 min read
 SubstancesIboga for alcohol addictionThe taper first, what the ceremony does, and the months after.25 min read
 SubstancesHow to quit cocaineThe crash, the craving, the heart first, and what the research shows.14 min read
- SubstancesHow to quit kratom and 7-OHOpioid-type withdrawal, tapering, and the cautions to know before iboga.11 min read
 SubstancesHow to get off Xanax and benzosWhy the taper comes first, and what iboga can offer after it.14 min read
 SubstancesHow to get off AdderallPrescription stimulants, the crash, ADHD after stopping, and the need to perform.13 min read
 SubstancesHow to quit ketamineDependence, the bladder, the low weeks, and coming back to yourself.13 min read
 SubstancesHow to quit weedCannabis withdrawal day by day, what works, and what the ceremony adds.14 min read
 SubstancesHow to quit smokingCigarettes, vapes and pouches: nicotine, the evidence, and the breath behind it.11 min read
 SubstancesChemsex recoveryTina, G and mephedrone, GHB withdrawal, and finding sober intimacy again.15 min read
 BehaviorsHow to stop gamblingSports betting, chasing losses, what works, and what a ceremony can add.16 min read
 BehaviorsHow to quit video gamesGaming disorder, the reward loop, what works, and coming back to real life.17 min read
 BehaviorsHow to quit pornCompulsive sexual behavior, OnlyFans spending, what works, and an honest word on iboga.19 min read
 BehaviorsHow to quit social mediaEndless scrolling, TikTok and Instagram, what works, and an honest word on iboga.15 min read
 BehaviorsHow to stop compulsive shoppingCompulsive buying, buy now pay later, help with debt, and an honest word on iboga.14 min read
 BehaviorsHow to stop binge eatingBinge eating disorder, food addiction, what works, and an honest word on iboga.14 min read
 BehaviorsHow to stop love addictionCodependency, anxious attachment, letting go, and an honest word on iboga.14 min read